Yes — type 2 diabetes can go into full remission. In remission, your blood glucose returns to the normal range without diabetes medication. For many people, that means no metformin, no insulin, and HbA1c readings that look like those of someone who never had the condition.
But the headline hides an essential detail: remission is most likely for a specific group of people, reached through specific methods, within a specific window of time. For others, the same approaches still dramatically lower blood glucose and reduce complications — even if full remission stays out of reach.
This guide explains exactly what remission means, why it happens at a cellular level, who is most likely to achieve it, and what the four proven pathways involve. You’ll come away knowing whether remission is a realistic goal for you — and what to discuss with your doctor.

What Does “Reversing” Type 2 Diabetes Actually Mean?
The word “reversing” has become shorthand for something more precise: remission. Researchers and clinicians settled on this term through a 2021 international consensus led by the American Diabetes Association, Diabetes UK, and the European Association for the Study of Diabetes.
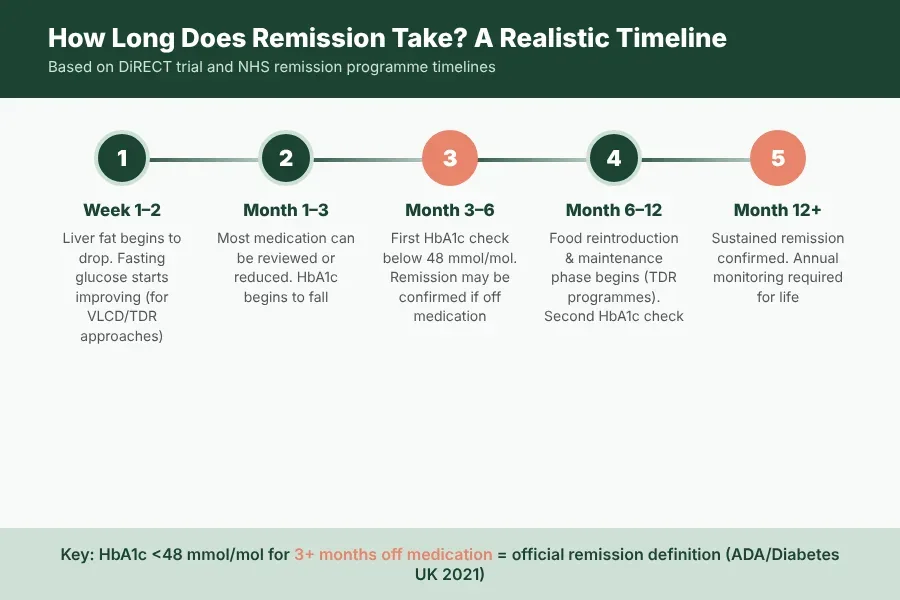
Remission is defined as an HbA1c below 48 mmol/mol (6.5%) that is sustained for at least three months — without any glucose-lowering medication.
That threshold matters. An HbA1c of 48 mmol/mol or above is the diagnostic cutoff for type 2 diabetes in the UK, Australia, and most of Europe (the US uses the equivalent of 6.5%). Dropping below it, off all medication, for three or more months means the condition is no longer clinically active.
Remission is not a cure
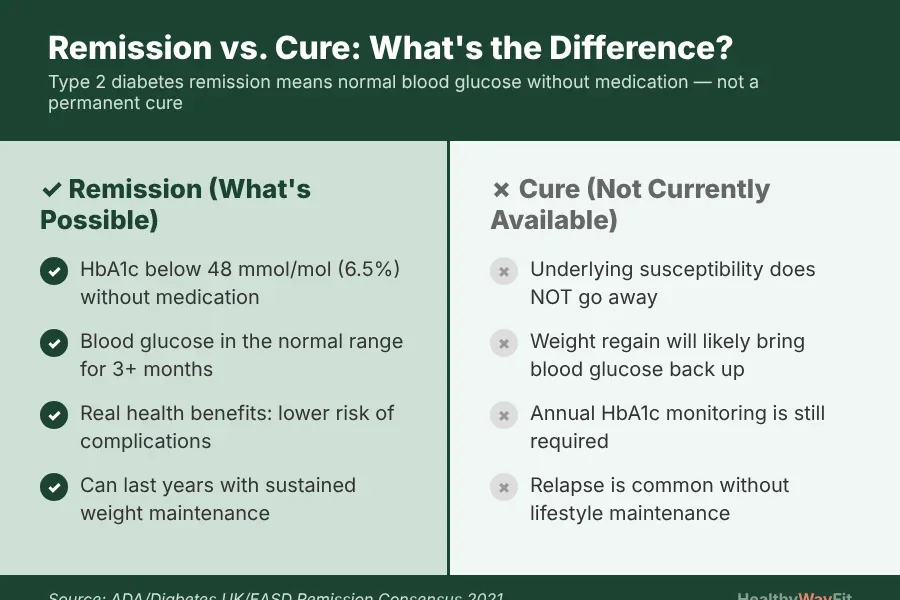
The underlying genetic susceptibility and physiological changes that made someone develop type 2 diabetes remain. If weight is regained, or old eating habits return, blood glucose will rise again. Relapse is common. This is why the consensus statement chose “remission” rather than “reversal” or “cure” — the same language oncologists use for cancer.
Partial vs. complete remission
The consensus also distinguishes between:
- Partial remission: HbA1c between 39–47 mmol/mol (5.7–6.4%) without medication — below the diabetes threshold but still in the prediabetes range.
- Complete remission: HbA1c below 39 mmol/mol (5.7%) without medication — fully normal blood glucose.
Both are meaningful. Both carry real health benefits. Complete remission is rarer and harder to sustain.
The Science Behind Remission: How Fat Chokes Your Pancreas
To understand why remission is possible — and for whom — you need to understand what causes type 2 diabetes in the first place.
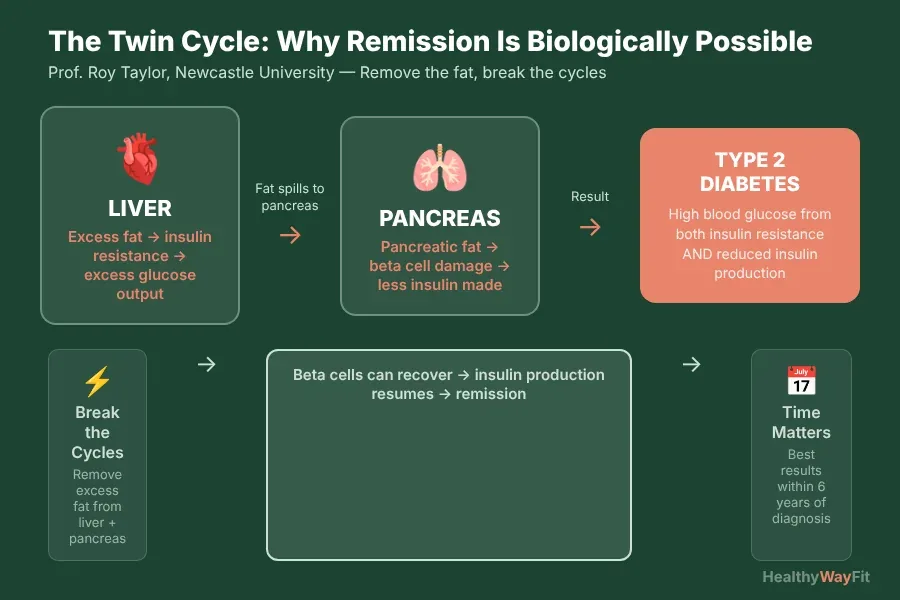
The best-supported explanation is the Twin Cycle Hypothesis, developed by Professor Roy Taylor at Newcastle University through decades of research. The theory works in two linked cycles:
Cycle 1 — The Liver: Excess calories (especially from refined carbohydrates and saturated fat) are stored as fat in the liver. This liver fat drives insulin resistance: the liver keeps releasing glucose even when blood insulin signals it to stop. The pancreas responds by pumping out more insulin. Over years, this chronic overdemand exhausts the system.
Cycle 2 — The Pancreas: Fat that overflows from a saturated liver is deposited in the pancreas. This pancreatic fat directly damages beta cells — the cells that produce insulin. Beta cell function declines. The combination of insulin resistance and reduced insulin production is what we call type 2 diabetes.
Here’s why remission is possible: remove the fat, and the cycles can reverse. Taylor’s Counterpoint Study (2011) demonstrated that an 800-calorie diet caused liver fat to fall within 7 days and pancreatic fat to normalise within 8 weeks — with beta cell function recovering substantially in people who had been diabetic for fewer than 4 years.
The critical word is can. If beta cells have been damaged long enough, they may not fully recover. That is why duration of diabetes is the single strongest predictor of who achieves remission.
Who Is Most Likely to Achieve Remission?
Not everyone with type 2 diabetes will achieve remission through lifestyle change alone. The evidence points to a consistent set of predictors:
1. Shorter diabetes duration
The DiRECT trial — the largest and most rigorous remission trial to date — found that people diagnosed within the last 6 years were significantly more likely to achieve remission than those who had lived with the condition for longer. At year one, 57% of those with fewer than 6 years’ duration achieved remission, compared with 34% of those with 6–10 years and a much lower proportion beyond 10 years.
Why? Beta cells. The longer they have been under stress from chronic high glucose and fat deposition, the less reserve they retain. Remission depends on recovering function that is still there.
2. Beta cell reserve (C-peptide)
A C-peptide blood test measures how much insulin your pancreas is still producing. Higher C-peptide at baseline means more functional beta cell reserve — and a much higher chance of remission. Some researchers now argue that C-peptide should be used to screen candidates for remission programmes before they start.
3. Not yet on insulin
Starting insulin typically signals advanced beta cell failure. It is not an absolute barrier — remission has been documented in people who began insulin — but it substantially reduces the odds.
4. Significant weight to lose (and the ability to lose it)
All lifestyle-based remission routes work through weight loss. The DiRECT trial required participants to have a BMI between 27 and 45 kg/m². People with a BMI in the normal range may have “lean T2D,” a different metabolic profile where fat accumulation occurs in the absence of obvious obesity, and the approach needs to differ.

5. Shorter time since diagnosis and fewer complications
Established complications (retinopathy, nephropathy) do not block remission from occurring, but they signal that the metabolic environment has been disrupted longer, and the underlying risks for those complications continue even during remission.
Four Pathways to Remission — What the Evidence Actually Shows
There is no single “right” way to achieve remission. Four approaches have robust clinical evidence. They share a mechanism — reducing fat in the liver and pancreas — but differ in how they get there.
1. Structured Weight Loss Programmes (The DiRECT Trial)
The Diabetes Remission Clinical Trial (DiRECT), funded by Diabetes UK and published in The Lancet, is the most cited remission evidence. Led by Taylor and Professor Michael Lean, it enrolled 298 adults with T2D diagnosed within 6 years and a BMI of 27–45.
The intervention: a total diet replacement (TDR) of 825–853 calories per day for 3–5 months using formula products (soups and shakes), followed by structured food reintroduction and long-term maintenance support.
Results:
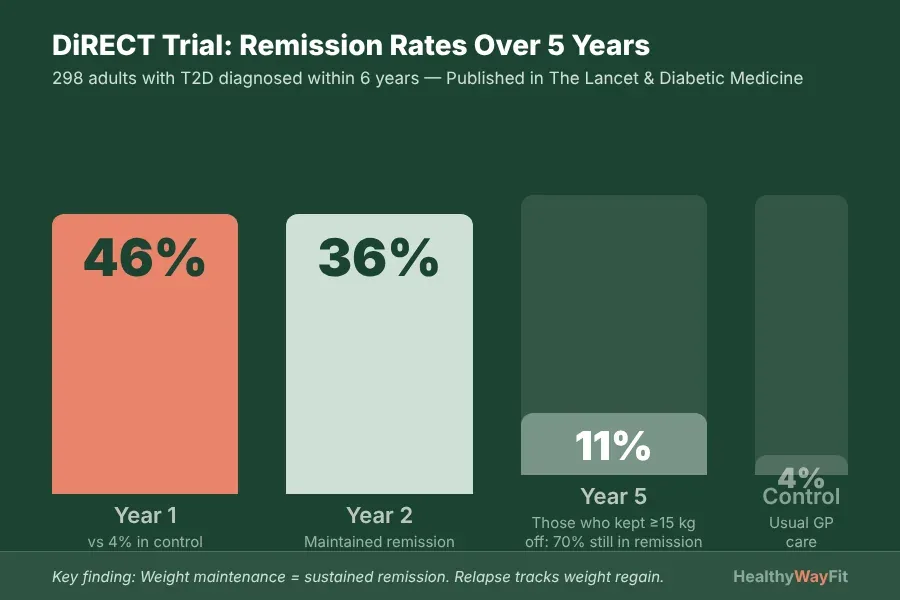
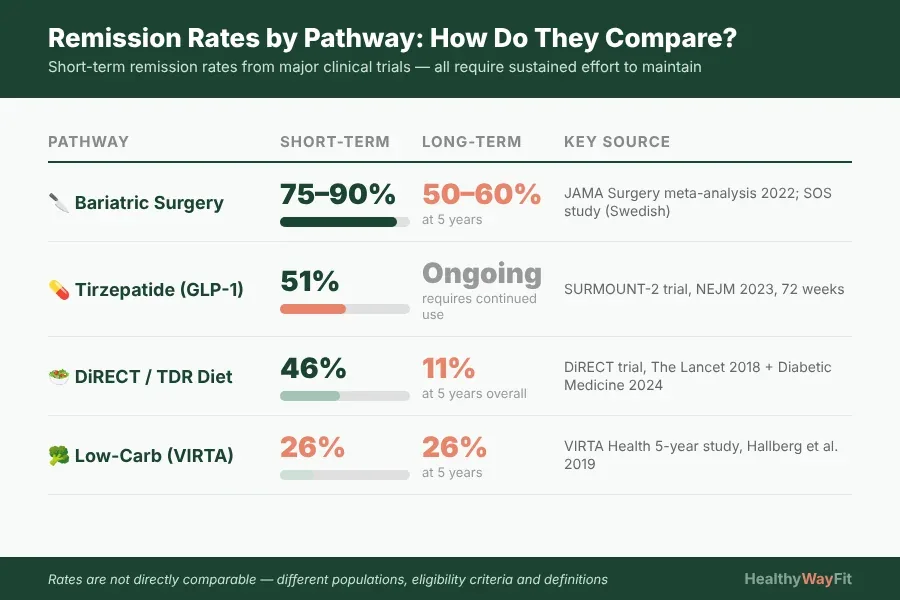
- Year 1: 46% of the intervention group achieved remission (vs. 4% in the control group)
- Year 2: 36% sustained remission
- Year 5: 11% sustained remission (published in Diabetic Medicine, 2024)
The drop from 46% to 11% over five years is often quoted as evidence that remission “doesn’t last.” That misreads the data: the majority of people who lost ≥15 kg and kept it off remained in remission. Remission lasted as long as the weight loss was maintained. The challenge is maintenance, not the biology.
The NHS Type 2 Diabetes Path to Remission Programme now offers this approach through the NHS in England and Scotland. A similar programme runs through Diabetes Australia and is available through select providers in Canada and the US.
2. Low-Calorie and Low-Carbohydrate Diets
Outside of total diet replacement programmes, two dietary strategies have strong evidence:
Very Low-Calorie Diets (VLCD): Consuming 800–1,000 calories per day through food (rather than formula products) produces similar liver and pancreatic fat reduction. The Look AHEAD trial and Taylor’s own Counterpoint Study support this route. Some individuals find food-based VLCDs more sustainable than formula-only approaches.
Low-Carbohydrate Diets: A 2-year RCT published in Frontiers in Endocrinology (2023) found that a carbohydrate-restricted diet (<26g net carbs/day) achieved remission in 17.6% of participants vs. 0% in the usual care group. The VIRTA Health trial — ongoing since 2015 — has documented 26% sustained remission at 5 years through continuous carbohydrate restriction with remote clinical support. For a detailed breakdown of the low-carb vs. low-fat evidence, see our guide on low-carb vs low-fat diets for diabetes.
The mechanism differs slightly: carbohydrate restriction reduces hepatic glucose output and insulin demand without necessarily producing the same total weight loss, which may explain why some people without significant obesity also respond.
3. GLP-1 Receptor Agonists (Semaglutide and Tirzepatide)
The newest and fastest-growing pathway to remission involves GLP-1 receptor agonists — a class that now includes some of the most studied weight-loss medications ever trialled.
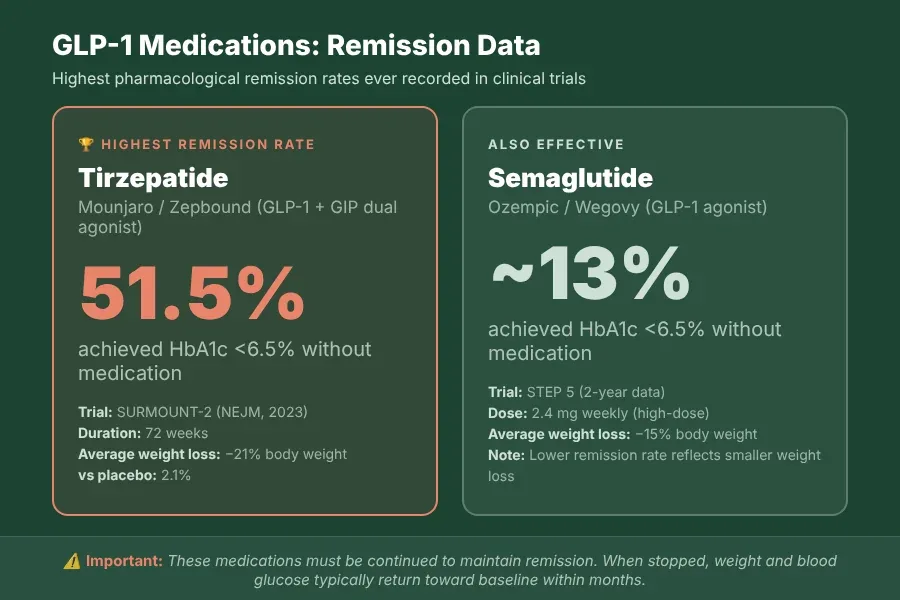
Tirzepatide (Mounjaro/Zepbound): The SURMOUNT-2 trial, published in NEJM in 2023, enrolled adults with type 2 diabetes and obesity. At 72 weeks, 51.5% of the high-dose tirzepatide group achieved HbA1c below 6.5% without medication compared to 2.1% on placebo. This is the highest remission rate ever documented in a pharmacological trial.
Semaglutide (Ozempic/Wegovy): The STEP 5 trial (2-year data) showed that high-dose semaglutide (2.4 mg weekly) reduced HbA1c to below 6.5% in approximately 13% of participants with T2D — lower than tirzepatide, reflecting a smaller average weight loss (−15% vs −21%).
An important caveat: these medications must be continued to maintain remission. When semaglutide is stopped, weight and blood glucose return toward baseline. These are remission tools, not one-time treatments. The long-term cost and availability of GLP-1s remains a practical barrier in many healthcare systems.
4. Bariatric (Metabolic) Surgery
Surgery produces the highest and most durable remission rates. A 2022 meta-analysis in JAMA Surgery found remission rates of 75–90% at 1–2 years for the most common procedures (Roux-en-Y gastric bypass and sleeve gastrectomy).
However, the 5-year picture is more modest: the Swedish Obese Subjects (SOS) study documented remission rates of approximately 50–60% at 5 years, declining further at 10 years, particularly after sleeve gastrectomy. The durability depends again on sustained weight maintenance.
Surgery is the recommended pathway for people with a BMI above 35 (or above 30 with significant complications) who have not achieved adequate glycaemic control through lifestyle and medical therapy. The UK, US, Australian, and European diabetes societies all include bariatric surgery in their remission pathway guidance.
How Long Does Remission Take?
There is no single timeline — it depends on the pathway and the individual — but the evidence gives a useful framework:
First signs (4–12 weeks): People following VLCDs or TDR programmes typically see fasting glucose begin to normalise within days to weeks. HbA1c, which reflects a 3-month average, takes longer to show the full effect.
First remission check (3–6 months): The ADA/Diabetes UK consensus requires HbA1c below 48 mmol/mol to be sustained for at least 3 months off medication before remission can be confirmed. Clinicians typically check HbA1c at 3–6 months.
Sustained remission assessment (12 months): The DiRECT trial and most clinical programmes define “sustained remission” at 12 months. This is when the HbA1c measurement most reliably reflects whether the underlying metabolic change has held.
Ongoing monitoring: Even people who achieve full remission require annual HbA1c monitoring. Relapse is possible at any point, particularly after weight regain or significant life stress.
What Happens After Remission — And How to Keep It
Remission without maintenance is temporary. The evidence is consistent: weight is the hinge. Regaining the weight you lost will bring blood glucose back up, often within months.
The DiRECT trial showed this clearly. Among people who maintained ≥15 kg of weight loss at 5 years, 70% remained in remission. Among those who regained weight, almost all relapsed.

Relapse risk factors
- Weight regain of ≥5 kg above lowest post-intervention weight
- Return to pre-intervention dietary patterns
- Reduced physical activity (which independently affects insulin sensitivity)
- Significant psychological stress or major life events (surgery, bereavement, illness)
- Certain medications that raise blood glucose (corticosteroids, antipsychotics, some antihypertensives)
Maintaining remission
The evidence-backed maintenance approaches include:
- Regular self-monitoring: Body weight weekly; HbA1c at least annually (more frequently in the first 2 years of remission)
- Continued structured support: People with access to ongoing group or individual support maintain remission at higher rates (DiRECT maintenance programme data)
- Physical activity: Aerobic exercise and resistance training both improve insulin sensitivity independently of weight, buffering against relapse
- Dietary quality: Focusing on the best foods for blood sugar control — rather than returning to refined carbohydrates and processed foods — is the single most modifiable long-term variable
- Psychological readiness: Identifying personal triggers for dietary relapse and having pre-agreed strategies has been shown to improve long-term outcomes in obesity management programmes
Questions to Ask Your Doctor About Remission
If you are considering pursuing remission, these are the most useful questions to bring to your next appointment:
- What is my current HbA1c, and how long have I had type 2 diabetes? (Duration is the strongest predictor of success)
- Can you check my C-peptide level? (This helps assess remaining beta cell function)
- Am I eligible for a structured remission programme? (Ask about NHS Path to Remission, DiRECT-based programmes, or equivalent national programmes in Australia, Canada, or the US)
- What diabetes medications am I on, and are any of them preventing me from trying dietary approaches safely? (Some medication combinations require careful medical supervision during rapid dietary change — particularly SGLT2 inhibitors and insulin)
- Would a GLP-1 medication be appropriate for me? (Relevant if BMI is over 30 and lifestyle approaches have not produced adequate results)
- What monitoring will I need if I go into remission? (Annual HbA1c at minimum; some clinicians recommend more frequent checks in the first two years)

Frequently Asked Questions
Can type 2 diabetes be reversed permanently?
Full remission can last for years, but it is not permanent in the way a cure would be. The underlying risk remains. Studies show that maintaining the weight loss achieved during remission is the key determinant of how long remission lasts — and some people do sustain it for a decade or more.
Can thin people reverse type 2 diabetes?
Yes, though the pathway is different. “Lean T2D” — type 2 diabetes without significant obesity — often involves ectopic fat (fat stored in organs rather than visibly under the skin). Low-carbohydrate diets may be more useful here than calorie-restricted weight loss programmes. This is an area of active research.
Does metformin prevent remission?
No. Metformin lowers blood glucose but does not accelerate beta cell decline. However, by the definition of remission (HbA1c below 48 mmol/mol without medication), you need to stop metformin before remission can be formally confirmed. This should be done under medical supervision.
What is the NHS remission programme?
The NHS Type 2 Diabetes Path to Remission Programme offers an evidence-based total diet replacement approach to eligible adults in England and Scotland. Eligibility criteria include a BMI of 27–45 (23–45 for South Asian, Chinese, other Asian, Middle Eastern, Black African, and African-Caribbean backgrounds), T2D diagnosed within the last 6 years, and not currently on insulin. Similar programmes exist through NHS Scotland, Diabetes Australia, and select Canadian and US providers.
Medical disclaimer: This article is for informational purposes only and does not constitute medical advice, diagnosis, or treatment. Always consult a qualified healthcare provider — such as your GP, endocrinologist, or diabetes specialist — before making any changes to your diabetes medication, diet, or management plan. Never stop or reduce diabetes medication without medical supervision.
Sources
- Lean MEJ, et al. Primary care-led weight management for remission of type 2 diabetes (DiRECT): an open-label, cluster-randomised trial. The Lancet. 2018;391(10120):541–551.
- Lean MEJ, et al. Durability of a primary care-led weight-management intervention for remission of type 2 diabetes: 2-year results of the DiRECT open-label, cluster-randomised trial. The Lancet Diabetes & Endocrinology. 2019;7(5):344–355.
- Lean M, et al. Five-year follow-up of the Diabetes Remission Clinical Trial (DiRECT). Diabetic Medicine. 2024.
- Taylor R, et al. Remission of type 2 diabetes: whole-body energy balance as the key target. Frontiers in Endocrinology. 2023.
- Taylor R, et al. Calorie restriction for long-term remission of type 2 diabetes (Counterpoint Study). Diabetologia. 2011;54(10):2506–2514.
- Lingvay I, et al. Tirzepatide versus insulin degludec in patients with type 2 diabetes (SURMOUNT-2). New England Journal of Medicine. 2023;388(8):693–703.
- Rubino DM, et al. Effect of continued weekly subcutaneous semaglutide vs placebo on weight loss maintenance in adults with obesity (STEP 5). JAMA. 2022;327(13):1269–1280.
- Buse JB, et al. 2019 Update to: Management of hyperglycemia in type 2 diabetes, 2018. Diabetes Care. 2019;43(2):487–493. (ADA/Diabetes UK remission consensus reference)
- Aminian A, et al. Association of bariatric surgery with major adverse liver and cardiovascular outcomes in patients with biopsy-proven nonalcoholic steatohepatitis. JAMA Surgery. 2022;157(3):229–237.
- Sjöström L, et al. Bariatric surgery and long-term cardiovascular events (Swedish Obese Subjects Study). JAMA. 2012;307(1):56–65.
- Hallberg SJ, et al. Effectiveness and safety of a novel care model for the management of type 2 diabetes at 1 year (VIRTA Health). Diabetes Therapy. 2018;9(2):583–612.